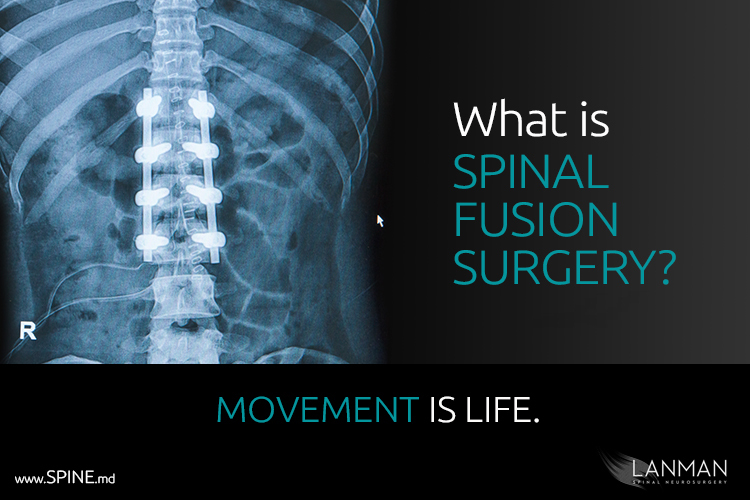
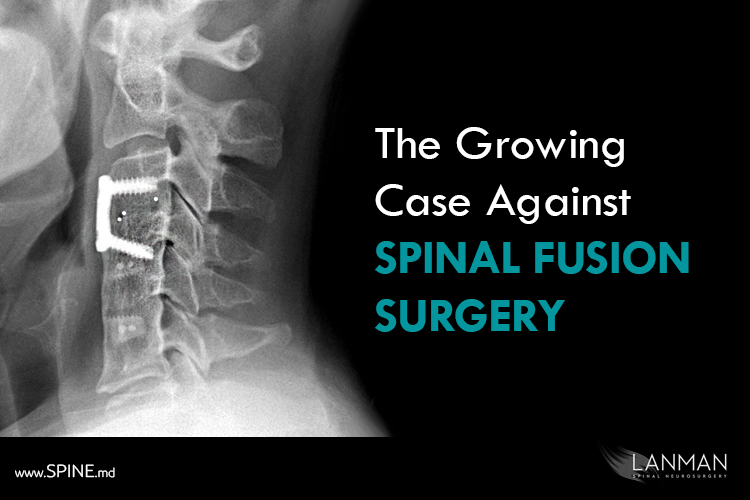
Spinal fusion can be an effective treatment for certain spine conditions, especially when a painful or unstable segment needs to be stabilized. However, fusion also changes how the spine moves. Once one section no longer has normal motion, the discs, joints, and nerves above or below the fused level may absorb more stress over time.
Adjacent segment disease, or ASD, occurs when the spinal levels next to a previous fusion begin to break down and cause symptoms. For some patients, this can lead to new pain, stiffness, numbness, weakness, or radiating nerve symptoms years after the original surgery. This guide explains why adjacent segment disease can develop after spinal fusion, what symptoms to watch for, and how the condition may be evaluated and treated.
Dr. Todd Lanman has extensive experience treating complex post-fusion spine problems, including cases in which patients develop new symptoms after a previous operation. His approach focuses on understanding the entire spine, identifying the true source of symptoms, and preserving or restoring motion when the patient’s anatomy and diagnosis support that option.
What Is Adjacent Segment Disease?
Adjacent segment disease, or ASD, is a condition that can develop when the spinal levels next to a previous fusion begin to break down and cause symptoms. After fusion, the treated section of the spine no longer moves normally. This can shift more mechanical stress to the discs, joints, and nerves above or below the fused area.
Some wear and tear in the spine can occur naturally with age, and not every change near a fusion is caused by the surgery itself. Adjacent segment disease refers to degeneration near a fused spinal segment that becomes clinically significant, often because the nearby level now has to absorb more motion and load over time. This can contribute to disc degeneration, facet joint arthritis, spinal narrowing, or nerve compression.
It is also important to distinguish adjacent segment degeneration from adjacent segment disease. Adjacent segment degeneration means that imaging studies show changes near a previous fusion, but those changes may not cause major symptoms. Adjacent segment disease means those changes are associated with pain, nerve symptoms, reduced mobility, or functional problems.
Why Can Adjacent Segment Disease Happen After Fusion?
Spinal fusion stops motion at a painful or unstable part of the spine so the area can be stabilized. When that segment no longer moves, the levels above and below have to handle more of the bending and load from everyday activities. This loss of motion at the treated level can shift more stress to the nearby discs and joints over time.
Over time, this extra stress can wear down the nearby discs and small facet joints, sometimes narrowing the space around the nerves and causing pain or nerve symptoms. Not everyone develops adjacent segment disease, but the risk is higher if nearby levels were already showing wear, if multiple levels were fused, or if the spine is not well aligned after surgery.
Age, bone health, activity level, and genetics also play a role. In many patients, adjacent segment disease develops because normal aging changes combine with the added stress at the levels next to the fusion.
Symptoms of Adjacent Segment Disease
Adjacent segment disease can cause new symptoms near the area of a previous spinal fusion. These symptoms may develop slowly over time or become more noticeable after a period of improved function. The exact pattern depends on which part of the spine is affected and whether the nearby discs, joints, spinal canal, or nerves are involved.
Possible symptoms include:
- New neck or back pain above or below the fusion
- Pain that travels into the arms, hands, hips, legs, or feet
- Numbness, tingling, or weakness
- Stiffness or reduced mobility
- Trouble standing, walking, lifting, or turning the neck
- Symptoms that worsen with activity or improve with rest
Symptoms can look different depending on whether adjacent segment disease develops in the cervical, thoracic, or lumbar spine. Cervical adjacent segment disease may cause neck pain, arm pain, hand numbness, weakness, or coordination problems. Lumbar adjacent segment disease may cause low back pain, hip or leg pain, numbness, weakness, or trouble standing and walking. Thoracic adjacent segment disease is less common, but it may cause mid-back pain, chest wall discomfort, balance changes, or nerve-related symptoms depending on the level involved.
How Long After Fusion Can Adjacent Segment Disease Develop?
Adjacent segment disease usually develops years after a spinal fusion, not immediately after surgery. In many studies, new problems at the levels next to a fusion become more noticeable within about 5 to 10 years, although some patients develop symptoms earlier and others much later, depending on their individual risk factors.
The timing can be influenced by several factors, including how many levels were fused, the condition of the nearby discs and joints before surgery, how well the spine was aligned, bone quality, and natural age-related wear and tear. As the levels above and below the fusion work harder over time, the discs, joints, and nerve openings can gradually wear out and start causing pain or nerve-related symptoms.
New or different pain years after a fusion should not be ignored, especially if it feels unlike your original symptoms or keeps getting worse. Pain that travels into the arms or legs, numbness, weakness, trouble with balance, or difficulty standing and walking for normal periods of time are all reasons to have your spine evaluated by a specialist.
How Adjacent Segment Disease Is Diagnosed
Diagnosing adjacent segment disease starts with understanding how a patient’s symptoms have changed since the original fusion. A spine specialist will review the prior surgery, the levels that were fused, how long ago the surgery took place, and whether the new pain, stiffness, numbness, weakness, or walking difficulty matches the spinal levels next to the fusion.
Imaging is often needed to confirm the diagnosis and identify the source of symptoms. X-rays can show spinal alignment, hardware position, disc space narrowing, and abnormal motion above or below the fusion. Flexion-extension X-rays, which are taken while the patient bends forward and backward, may help detect instability. MRI can evaluate the discs, nerves, spinal canal, and soft tissues, especially when symptoms suggest nerve compression. CT may be useful when the surgeon needs a clearer view of bone, prior hardware, or whether the original fusion has healed properly.
A careful diagnosis matters because not every imaging change near a fusion causes symptoms. Some patients have adjacent segment degeneration without pain or nerve problems. Adjacent segment disease is diagnosed when the changes near the fusion match the patient’s symptoms and affect comfort, mobility, nerve function, or quality of life. Dr. Lanman evaluates the entire spine, including alignment, motion, nerve compression, and prior surgical history, to determine whether symptoms are truly related to adjacent segment disease and which treatment options may be appropriate.
Treatment Options for Adjacent Segment Disease
Treatment for adjacent segment disease depends on the severity of symptoms, the location of the affected level, and whether nearby nerves or the spinal cord are compressed. Some patients improve with non-surgical care, while others may need surgery when pain, weakness, or loss of function becomes significant.
Non-Surgical Care
Many people with early or mild adjacent segment disease can manage symptoms without another surgery, especially when there is no severe pressure on the nerves or spinal cord. Non-surgical care aims to reduce pain, improve movement, and keep you as active and independent as possible.
Common options may include:
- Physical therapy focused on gentle stretching, core and back strengthening, and posture training
- Activity modification, such as avoiding heavy lifting or repetitive bending that flares symptoms
- Anti-inflammatory or other pain-relieving medicines, when appropriate
- Guided home exercise programs to maintain flexibility and strength between visits
- Targeted spinal injections to reduce inflammation around irritated joints or nerves when pain is more severe
These treatments do not reverse the structural wear-and-tear at the nearby spinal levels, but they can make a meaningful difference in day-to-day comfort and function. For many patients, a period of consistent non-surgical care is an important first step and may delay or even eliminate the need for additional surgery.
Surgical Options When Symptoms Progress
Surgery may be considered when adjacent segment disease causes significant pain, nerve compression, weakness, or loss of function that does not improve with non-surgical care. The goal is to relieve pressure on affected nerves or the spinal cord, restore stability when needed, and address the source of pain while preserving as much healthy spinal motion as possible.
Surgical options may include decompression, extension of the prior fusion, artificial disc replacement, or other motion-preserving procedures. In select complex cases, Dr. Lanman may also evaluate whether a problematic prior fusion can be revised or reversed and treated with artificial disc replacement. He has helped pioneer advanced revision strategies for patients who were previously told that another fusion was their only option.
The right approach depends on the location of the adjacent segment disease, the patient’s alignment, bone quality, facet joint health, nerve compression, and details of the previous surgery. Dr. Lanman’s experience with complex post-fusion revision and motion-preserving spine surgery allows him to consider a broader range of options for properly selected patients.
Can Artificial Disc Replacement Help Prevent Adjacent Segment Disease?
Artificial disc replacement is designed to treat a damaged spinal disc while preserving motion at the treated level. Unlike fusion, which locks two or more vertebrae together, artificial disc replacement allows the operated segment to continue moving in a more natural way.
Because artificial disc replacement does not intentionally eliminate motion, it may reduce mechanical stress on the nearby spinal levels compared with fusion in properly selected patients. This may help lower the risk of adjacent segment problems over time.2
Dr. Lanman is known for his focus on motion preservation, including artificial disc replacement and other advanced non-fusion approaches. For patients who already had fusion, he also evaluates whether motion-preserving revision options may be possible, depending on the patient’s anatomy, alignment, prior surgery, and source of symptoms.
When to See a Spine Specialist After Fusion
Patients should consider a spine evaluation if they develop new or worsening symptoms after a period of improvement from spinal fusion. This is especially important when pain starts to travel into the arms or legs, or when symptoms begin to interfere with walking, standing, work, exercise, or daily activities.
A specialist evaluation may be appropriate for symptoms such as weakness, numbness, tingling, coordination problems, reduced mobility, or pain that persists despite conservative care. These symptoms may suggest that the adjacent spinal levels, nearby nerves, or spinal cord need closer evaluation.
Severe weakness, loss of bowel or bladder control, rapidly worsening neurological symptoms, or major changes in balance or walking should be addressed urgently. These signs may indicate significant nerve or spinal cord compression that requires prompt medical attention.
Get Expert Help for Post-Fusion Spine Problems
New or changing pain after spinal fusion deserves a careful, whole-spine evaluation, not just a quick look at the fused level. A thoughtful assessment should consider your spinal alignment, disc and facet joint health, nerve compression, bone quality, and the long-term effects of the original fusion on nearby levels.
Dr. Todd Lanman focuses on complex post-fusion cases and motion-preserving strategies when they are safe and appropriate. If you are noticing new pain, stiffness, weakness, numbness, or trouble with daily activities years after fusion, you can schedule a consultation with Dr. Lanman to better understand what is causing your symptoms and which treatment options may make sense for you.